About Eugenie Lee

Eugenie Lee is a CripQueer, autistic, 1.5th-generation Korean-Australian interdisciplinary artist living on Wangal Land (Sydney, Australia). Her conceptual research explores reimagined storytelling and antidotes to stigmatised human conditions with which she has intimate experience, such as persistent (chronic) pain, post-colonial medical misogyny, hidden disability, and diaspora. She collaborates with partners across the sciences, humanities, creative technologists, and communities of lived experience as an essential part of her creative process. She recontextualises deeply personal topics through multi-layered intersectional perspectives of phenomenology and cross-disciplinary research into experimental artworks, including intimate 1:1 participatory performances, installations, sculptures, and paintings.

INFLAMMATION

The more I do research, the more I come across the topic of inflammation. It is clear that menopause and aging are intrinsically linked to inflammation.


Here are friendly easy resources to learn more about inflammation – I tried reading scientific literature about inflammation but it’s a serious mind-boggling #(%*&$@(%. I can’t even get a simple definition of inflammation in plain English. When I came across the resources below, I was relieved and delighted.

ZOE Science & Nutrition | 4 foods that heal your gut and reduce inflammation (in as little as 24 hours!) | Dr Will Bulsiewicz

https://www.podbean.com/ea/dir-q7inj-2a7efc34

Or a YouTube version https://www.youtube.com/watch?v=I6jQgIjuNHU


James Nestor’s book, ‘Breath’, entertainingly shares stories and scientific studies on breathing correctly to drastically improve our wellbeing and reduce anxiety and stress, which, in turn, calm chronic inflammation. On his website, he freely shares audio breathwork if you sign up.

https://www.mrjamesnestor.com/audio


ZOE Science & Nutrition | The daily step count that cuts inflammation in half | Prof. Janet Lord

https://www.podbean.com/ea/dir-zzyzn-261200a0


OTHER LINKS I ALSO LOVED:

ZOE Science & Nutrition | Davina McCall: Make this choice every day to reduce menopause symptoms

https://www.podbean.com/ea/dir-6393v-21bcb3f5

ZOE Science & Nutrition | Fix your sleep with the Royal Marine’s sleep consultant Dr. Sophie Bostock

https://www.podbean.com/ea/dir-uwwwk-27ab4cd6

GUT HEALTH

(NOTE: ‘women’ in this project refers to individuals who identify as such and/or are born with a genetic makeup that necessitates undergoing the female menopausal transition – peri-menopause, menopause, and post-menopause. For convenience, I will use the term ‘menopause’ to encompass the whole transition and the second half of women’s lives.)


This is a highly under-researched area. When I initially started researching menopause, the valid resources listed common symptoms but never included disrupted digestive issues, let alone the microbiome.

a street view of a building

Robinson Research Institute, Adelaide University

A reception with grey carpet and a large plaque

At the reception of Robinson Research Institute, waiting to see Prof David MacIntyre

I began to collaborate with Prof David MacIntyre, Robinson Research Institute, Adelaide Uni, to explore this fascinating topic. Robinson Research Institute has been primarily focusing on the female reproductive system, including, for example, postnatal depression. Research shows that women who experience postnatal depression are more likely to have severe menopausal symptoms later on. I am curious how their microbiome plays a role in this. Emerging research also says that women with endometriosis and adenomyosis, and/or who have taken contraceptive pills, have highly imbalanced gut microbiomes.

An adelaide uni plaque

While waiting to see Prof David MacIntyre, I noticed a plaque at the Robinson Research Institute. I had a burning desire to write “Menopause Research” with a permanent marker there. I wish I had a marker with me. Would I get away with it if I did write it?

When Dr Carolyn Berryman and I met David for the first time, we discussed his current research on the microbiome of women with endometriosis, and he was also interested in the full lifespan of women’s gut microbiome, including menopause. This got me very excited, and I look forward to exploring this further with him later. I am going to ask him about women with endometriosis and how this may play a significant role in their menopause, because for some women, endometriosis continues after they reach menopause. But there is still so much unknown about endometriosis, let alone menopause; I would be surprised to get clarity on this. I will cover the content of our next meeting in future posts.

three people sitting in an office

From right: Prof David MacIntyre, Dr Carolyn Berryman, Eugenie Lee

In the meantime, I’ve been doing my own research. Here is what we know so far about the relationship between menopause and the gut microbiome:

https://zoe.com/learn/gut-microbiome-menopause-changes

According to Zoe Science & Nutrition, our gut is a hormone factory. If we don’t look after our gut, the delicate balance of hormones will be disrupted, affecting our brain, inflammation, metabolic health, and overall wellbeing, including menopause.

As women transition into menopause, the oestrogen that has been supporting our gut health declines, leading to many gut and brain issues (anxiety, depression, memory, and executive functions).

Zoe’s podcast, episode (2 July 2 2026 issue) – ‘How to build a better brain: The 5 foods you need to protect your memory, mood and to cut dementia risk | with Felice Jacka (Professor of neuropsychiatry) and Tim Spector (Professor of Genetic Epidemiology).

https://www.podbean.com/ea/dir-k6d63-2f23ab13


Another research material I’ve found is a book titled ‘The Menopause Gut’ by Cynthia Thurlow. Here is a downloadable short info to learn about four gut types for menopausal women.

https://assets.cdn.filesafe.space/KoVj9BZlFtLUyD4Z4uVi/media/69c2545a427f6e27fd66d568.pdf


4 things you can do today to improve your immunity – interview with gastroenterologist Dr Giulia Enders.

https://www.youtube.com/watch?v=dVTF1xRt3sw

I am currently reading her two books, ‘Gut’, and ‘Organ Speak’. She also did a Netflix documentary called ‘Hack Your Health: The Secrets of Your Gut’.

SYMPTOMS OF MENOPAUSE & MIND MAP

(NOTE: ‘women’ in this project refers to individuals who identify as such and/or are born with a genetic makeup that necessitates undergoing the female menopausal transition – peri-menopause, menopause, and post-menopause. For convenience, I will use the term ‘menopause’ to encompass the whole transition and the second half of women’s lives.)


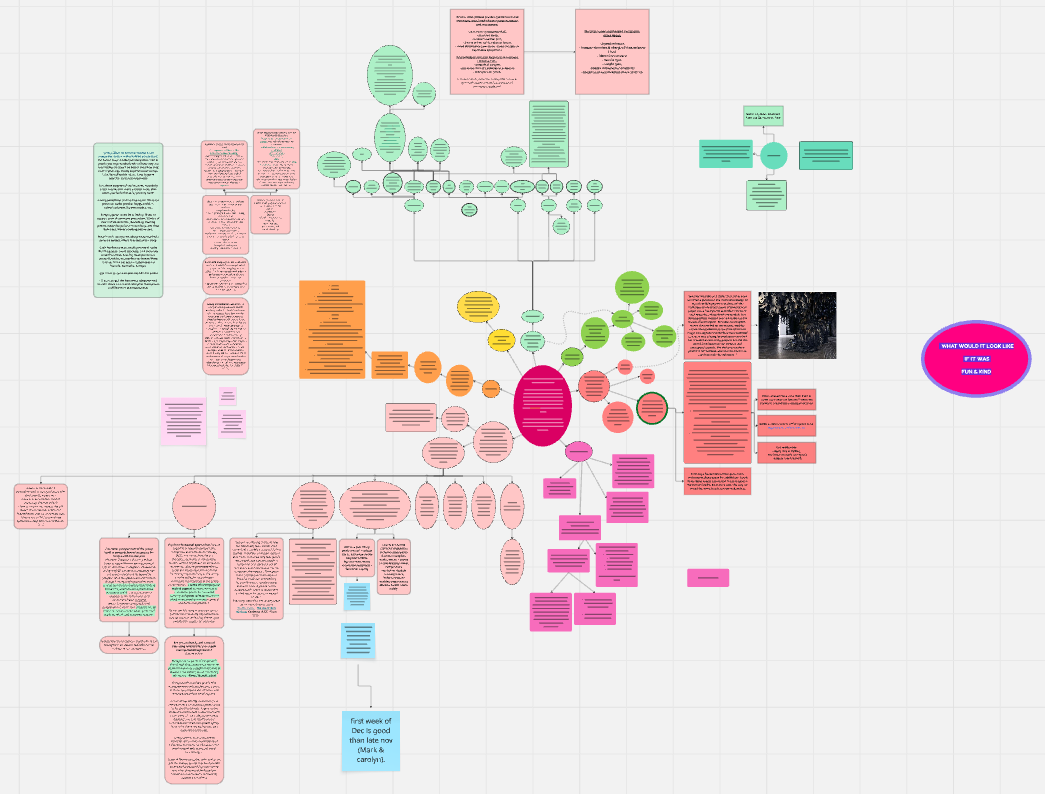
I have gathered common symptoms of menopause according to the current scientific literature.  Here is the mind map to visualise the symptom categories.

colourful bubbles with lots of text. Each bubble is linked by lines to other bubbles.

Mind map to list official menopausal symptoms and recommended treatment options, alongside my collaborators and my thoughts.

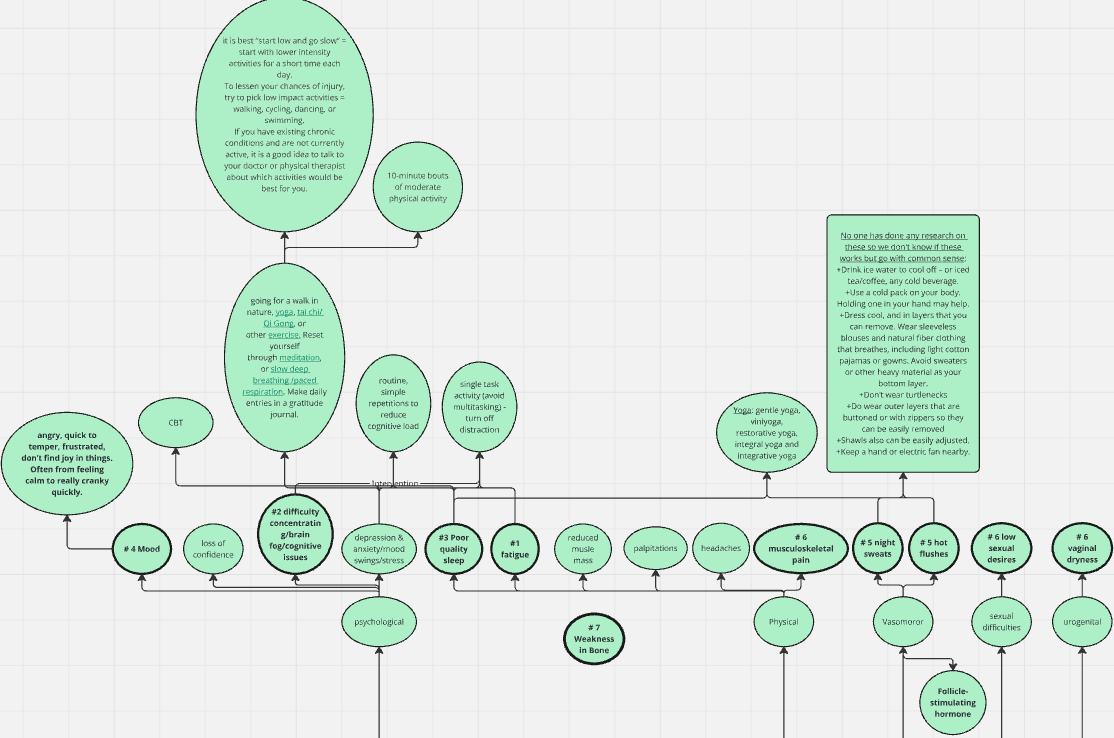
Close up for the official symptoms:

Green bubbles with text

The official symptoms of menopause. Depending on research, some of these symptoms are either excluded or included.

But more I do research and listen to the lived experience, the more I think the officially acknowledged symptoms are rather short.

It is evident the official list is a work in progress, because depending on the paper, some researchers mention only a few symptoms; for example, some say mental health, including anxiety and depression, is NOT a part of menopause, while others vehemently disagree. I happen to tick most of the boxes on the list for my own symptoms, AND have some more –

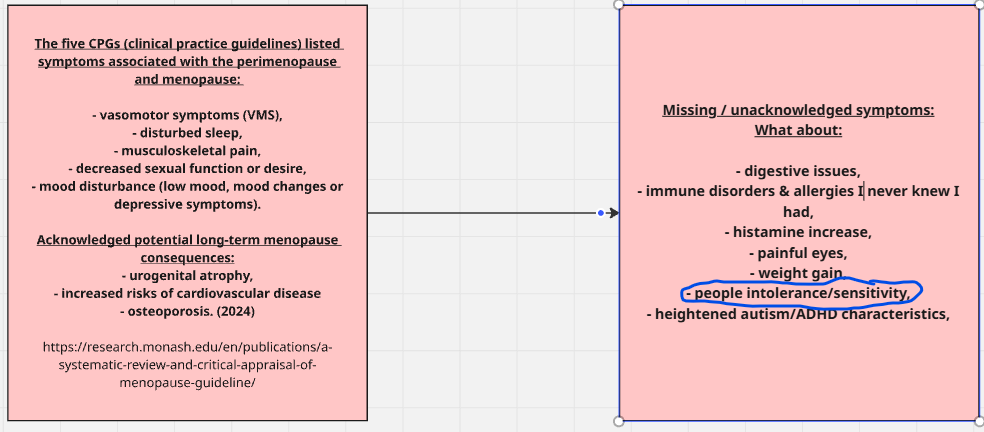
Note the blue circle below. When I mention this to all the women I’ve spoken to, most women say ‘oh yeah…’ with a knowing nod when I mention them.

Two pink rectangular bubbles. and a blue circle on the right.

The left text is the condensed version of the officially recognised menopausal symptoms. On the right is the ones I could list that should be included.

People intolerance. I’m no longer tolerant of certain behaviours I see in people around me. It gives metaphorical hives and nausea. Perhaps it’s turning into an allergy. Many would verbally express it as “I’m done with that (or you)”. It is a nice form of an allergy. All ajumma must have this allergy. If you have this allergy, you are an ajumma. I love you.

Since I’ve created the mind maps, there has been an update. According to the largest menopause study by Zoe from the UK, there are now 38 known menopausal symptoms. But people intolerance isn’t one of them yet. It should be.


RESOURCES FOR MENOPAUSE EDUCATION

(NOTE: ‘women’ in this project refers to individuals who identify as such and/or are born with a genetic makeup that necessitates undergoing the female menopausal transition – peri-menopause, menopause, and post-menopause. For convenience, I will use the term ‘menopause’ to encompass the whole transition and the second half of women’s lives.)


Australian-based info (weeks – months’ worth of great info here):

https://wellfemme.com.au/about/

https://wellfemme.com.au/guides-and-fact-sheets/

https://wellfemme.com.au/wellfemme-webinars/


Free app for Australian menopause support, created by Dr Cari Cashell  with evidence-based info & community:

https://www.healthyhormones.au/


Dr Louise Newson, a UK-based menopause expert, providing free worldwide educational resources, including a free app & podcast:

https://www.drlouisenewson.co.uk/


The one and only Dr Kelly Casperson, a US-based urologist and a menopause expert. Her podcast is a must with information and a smile:

https://kellycaspersonmd.com/

I got her Audible called ‘The Menopause Moment’. It was so good, but I will need to buy the physical book as well so I can highlight and write notes.


Zoe’s MenoScale – a free online tool – to score where you are at with your Menopausal Symptoms. It takes approx. 2 mins with downloadable dietary guidance.

https://zoe.com/menoscale?lead_id=1a6e6254-b051-475b-a597-916bdd7db336

ZOE Science & Nutrition | How to track your menopause symptoms | Dr. Sarah Berry and Tamsen Fadal

https://www.podbean.com/ea/dir-sdqct-229c6a9d


Lisa Mosconi – A pioneer for the female brain, brain nutrition, and Women’s health. She’s written a book called ‘The Menopause Brain’, and ‘Brain Food’.

https://www.lisamosconi.com/

COMMON THREADS THAT BIND WOMEN UNDERGOING MENOPAUSE

(NOTE: ‘women’ in this project refers to individuals who identify as such and/or are born with a genetic makeup that necessitates undergoing the female menopausal transition – peri-menopause, menopause, and post-menopause. For convenience, I will use the term ‘menopause’ to encompass the whole transition and the second half of women’s lives.)

This is an ongoing topic throughout my R&D. For now, I’ll add a few key research pointers here, so I can remind myself whenever I need a refresher.


  • “menopause has a funny way of forcing us to grow. It asks us to advocate for ourselves, establish boundaries, prioritise our health, and step into the next chapter with intention. Looking back, some of the hardest lessons have also been some of the most transformative.


  • So much of the menopause conversation centres around what we’ve lost, what hurts, what changed, or what wasn’t there for us. Those stories matter and deserve to be told. But there’s something incredibly powerful about asking women what they want.


  • What do we want healthcare to look like? What do we want aging to look like? What do we want for our daughters and granddaughters? What would it feel like to be informed, supported, strong, vibrant, and seen?


  • For many women, menopause becomes less about decline and more about awakening. It pushes us to learn, advocate, set boundaries, prioritise our health, and become the author of our next chapter.


  • While the symptoms may differ, so many women share the same experience of feeling confused, dismissed, unprepared, or simply wondering, “Why didn’t anyone tell me this?”


  • Menopause is so much more than hot flushes. It’s identity, relationships, confidence, grief, resilience, reinvention, and discovering a strength we didn’t know we had.


  • Menopause is often talked about as a disease and seen through symptoms (with 38 known symptoms), but it’s a major growth period in the second half of women’s life trajectory. This period needs education, anticipatory guidance/preparation, and support. – food, diet, rest, mental health, reduce stress. How to augment their health for the rest of their lives? Normalise conversations about menopause; no mystery or hesitancy around it. “How do you feel?” is often missing in the menopause conversation – quality of life.


  • The brain is the biggest source of intimacy.


  • Estrogen is everywhere throughout the body. Lower estrogen levels affect our brain first. And then skin and muscles (including the vagina and vulva), and organs.


  • Weight distribution changes and weight gain can also affect psychological, cultural, economic, and social conversations; this needs to happen as women’s bodies change.


  • Weight gain has nothing to do with willpower (or the lack of).


  • Disrupted sleep: 8 out of 10 can be all-consuming and affect the entire day. Also brings brain fog. It directly impacts how they process/metabolise food, heightens reward centres in the brain, and leads to quick fixes for bad food, which in turn worsens sleep. Worsens other menopause symptoms.


  • Higher diet quality reduces symptoms by 20- 30%. Diverse plants that feed the gut and improve the microbiome are key. This is a relatively new area of study but promising. But there is no silver bullet that makes everything better.


  • Everything is inter-related. That means if one thing isn’t working, it can negatively affect the rest. It also means that if one thing improves, the rest can also follow positively.


  • Be selfish! Self-care is needed. Make the best decision for yourself. Small, bite-sized changes/improvements are key. For example:
    • Exercise snacking (eg, Feel Good With Lavina), including 1 min of tiny movement snacking throughout the day can be just as effective as 45min intensive gym sessions.
    • Balance, weight-bearing movements (stair climbing, fast walks, hopping, standing on one leg)
    • A short boogie down in the morning has been studied to benefit sleep.


  • HRT is better to be taken through skin (transdermal) absorption – that’s because it does not go through the liver first, rather than pills (oral) that go through the liver.


  • Menopause is the time when women’s health begins to shift. In the pre-menopausal state, women’s health has generally lower risk factors compared to men. Men’s health risk factors steadily increase as they age. But when women are in menopausal transition, their health risk factors dramatically increase, catch up to men’s risk factors, and can shoot up for the worse.


  • Eating healthy, diverse plant-based foods, fermented foods, and healthy oils can reduce risk factors.


  • Ethnicity, race, and access can affect women’s experience. Important to adapt for cultural sensitivity.


  • Many Asians experience fewer hot flushes due to particular microbes that can convert food chemicals that bind to estrogen receptors. Very early stage of study.

THE BASICS OF HORMONES IN MENOPAUSE (Part 2)

(NOTE: ‘women’ in this project refers to individuals who identify as such and/or are born with a genetic makeup that necessitates undergoing the female menopausal transition – peri-menopause, menopause, and post-menopause. For convenience, I will use the term ‘menopause’ to encompass the whole transition and the second half of women’s lives.)


  • In conjunction with the hormonal top-up, evidence shows there are many other proactive steps we can take, which my collaborators and I are exploring for narrative development.
  • The current recommendations suggest improving physical activity, sleep, stress management, and nutrition. Easier said than done, so we need extra support and knowledge in these areas.
  • Hormones are present throughout our bodies. We have always had them. We need them to survive and function well. Balanced hormones help keep us well.
  • During the menopause transition, hormones fluctuate and eventually decline significantly. Menopause affects the whole person, not just the reproductive organs, such as the ovaries. We should never underestimate the impact of diminishing hormones, as these issues are real. Here is a good resource in plain English, along with actionable advice. https://www.youtube.com/watch?v=DvT6NNpwA0I&t=56s
  • You can find out your own menopause symptom scores here for free. It is called ‘MenoScale Score’ – developed by the team of scientists from ZOE, as the result of the world’s largest menopause study into the link between diet and menopause: https://zoe.com/menoscale?lead_id=51fc5152-b38d-412f-89bb-563af650ae1b
  • Too often to this day, women are discouraged from exploring HRT options by untrained doctors. Be prepared to ask for second, third, and fourth opinions if this is the case. Don’t give up.
  • Trained doctors provide evidence-based information about HRT. They encourage women to make an informed choice about whether they want a top-up.
  • Here is a growing list of menopause doctors in Australia: https://www.healthyhormones.au/c/find-a-doctor/menopause-doctors-c452a877-11d5-45f3-a51f-7413aa160ca3
  • And here, particularly suitable for telehealth for menopause support: https://wellfemme.com.au/
  • Hormones play an important protective role. When hormones are no longer there, there will be some long-term health consequences we need to be aware of; therefore, we should never dismiss women’s menopause-related concerns. Some of the health consequences are:
  • cardiovascular disease (e.g., stroke, high blood pressure),
  • neurodegenerative diseases (e.g., dementia, Parkinson’s),
  • mood disorders (e.g., depression, anxiety, suicide ideation),
  • inflammations (e.g., joint pain, autoimmune disorders, overactive Mast Cells),
  • musculoskeletal diseases (e.g., osteoporosis),
  • digestive issues (e.g., IBS, constipation, Crohn’s),
  • Urogenital dysfunctions (e.g., UTI, pelvic pain),
  • Even some cancers, and
  • Worsening neurodivergent characteristics (hormone changes can cause profound effects on their brains, particularly on neurodivergent women, and it is one of the reasons why many women are diagnosed as neurodivergent in their perimenopause) https://www.podbean.com/media/share/dir-gudtd-2fb72336?utm_campaign=a_share_ep&utm_source=a_share_dir&utm_medium=dlink

THE BASICS OF HORMONES IN MENOPAUSE (Part 1)

(NOTE: ‘women’ in this project refers to individuals who identify as such and/or are born with a genetic makeup that necessitates undergoing the female menopausal transition – peri-menopause, menopause, and post-menopause. For convenience, I will use the term ‘menopause’ to encompass the whole transition as well as the second half of women’s lives.)

It is impossible to do research on menopause without coming across hormones. Here are some of the things I have learned so far:


  • Every woman deserves to know about hormones with the latest evidence-based knowledge, so they can make an informed choice whether to have hormonal top-up during the menopause transition.
  • Here is a conversation between Dr Louise Newson (a renowned UK menopause expert) and Dr Ceri Cashell (Australian GP and advocate for menopause) about the basics of hormones and the current situation of menopause: https://www.healthyhormones.au/c/live-events-e4b85e/power-of-hormones
  • We need well-balanced hormones to function throughout our lives. If hormones are imbalanced, our lives can get awful in every direction, because hormones are present everywhere in our body.
  • It comes down to women telling their experiences to clinicians, who listen and judiciously diagnose them for perimenopause. But it gets tricky. Many clinicians are not trained enough to identify perimenopausal symptoms, so there are plenty of undiagnosed, unsupported, and/or misdiagnosed perimenopausal women out there right now, struggling alone to make sense of their changing bodies and brains.
  • Medical schools globally teach menopause for 30 minutes – 3 hours in their entire medical training. Some universities only include menopause in a footnote.
  • Research shows that one of the best baselines for women’s functioning is to top up the adequate levels of hormones we lose as we age – body-identical hormones such as oestradiol, progesterone, and testosterone. They are called HRT (Hormone Replacement Therapy), also referred to as MHT (Menopausal Hormone Therapy), and HT (Hormonal Therapy).
  • The menopause experts state that HRT should be considered the first line to support menopausal women, not antidepressants. Yet many clinicians are more comfortable prescribing antidepressants to address many menopausal symptoms than supporting their low hormonal symptoms with a hormonal top-up. Here is a standard example most of the menopause experts share: A woman with night sweats and hot flushes keeps waking up several times at night for weeks, months, or years. Losing sleep like this, she is understandably at the end of her tether whilst expected to perform consistently well at work and care for her family. She keeps losing focus and energy. She has crazy brain fog. Her food intolerance and pooping problems also appear. She asks her doctor for help. To address all the varying symptoms, many doctors routinely prescribe antidepressants – a band-aid approach – which do nothing for the night sweats, hot flushes, brain fog, and gut issues. Whereas the right balance of HRT can. Antidepressants adversely block existing hormones from functioning.
  • The media announced in 2002 that the Women’s Health Initiative (WHI) trial on synthetic hormones reported that all HRT gives women breast cancer. This study was flawed and further misconstrued by the media. But overnight, millions of women around the globe stopped using HRT. Medical students, globally, have also missed out on learning about HRT and menopause ever since to this day. Not that there was much attention to menopause studies to begin with, but even this dismal amount of study got taken out of their curriculum. This fear-mongering misinformation remains the dominant medical knowledge today. Soon after the report was released, the researchers involved in the original study revealed its flaws, but no one heard them, nor did the media rectify the damage they’d caused. Many of the current medical professionals in menopause advocacy – such as Dr Mary Claire Haver, Dr Kelly Casperson, Dr Louise Newson, and Dr Ceri Cashell – have openly said they were self-taught in menopause studies because they were never taught in their years of medical training. Although they worked in the menopause field, they themselves were blindsided by their own perimenopause symptoms. Many of these incredible medical practitioners now provide education to other clinicians and to the public, disseminating accurate, evidence-based information.
  • My mother missed out on HRT support because of the WHI conundrum. My aunties and all the other women who had cared for me have also missed out. They now have a long list of serious illnesses. I can’t stop wondering if they had taken HRT, whether their devastating daily struggle could have been more manageable, or even prevented. The more I learn about this area, the more it breaks my heart. I know HRT is not a panacea, but I also know now that a hormone top-up can never be underestimated for optimising our body functions and mental health. It provides an excellent baseline so we can move forward with what we want to do throughout the second half of our lives.
  • Body-identical hormonal therapy, which most HRT is these days, comes with very low risk and can effectively support many symptoms. If women didn’t like them, they could stop taking them anytime and naturally return to their menopausal state with their usual symptoms within days, without any hang-ups. On the other hand, antidepressants actively suppress hormones and come with many side effects. They have never supported common symptoms like hot flushes, headaches, sleep, and digestive issues, yet these medications have often been the go-to prescriptions since the 2002 WHI incident. If women (or men) didn’t like them, it could be a hellish shitshow to come off them.
  • Almost every woman in their menopause transition, with a very small percentage of exceptions, is safe to take HRT. Because HRT is body-identical, it’s cheap to produce and cheap to buy. Pharmaceutical companies can’t profit from HRT.
  • Bio-identical oestradiol patches/cream/gel are mostly derived from wild yams or soy. The synthetic estrogen tablets from olden days for the WHI study in 2002 were derived from pregnant horses’ urine at a very high concentration, called Conjugated Equine Estrogens (Premarin). These are not the same types of estrogen as what we use now.
  • The human body naturally produces estradiol. We do not produce Premarin. Beware of lumping all ‘estrogens’ into one box. If it gets too confusing, just remember estradiol. Estradiol specifically is the anti-inflammatory hormone. This is the good estrogen type. This is the one we had in abundance when we were younger, smoother, tighter and healthier. We lose this as we get older, and topping up with this one is a good idea. Estradiol.
  • We need to top up with progesterone, testosterone, and estradiol, as they work synergistically. Progesterone is estradiol’s trusty sidekick. We need it, even if women no longer have a uterus.
  • Women have more testosterone than estrogen. So most menopausal women also need a testosterone top-up. All three work together.
  • Except for a very small percentage of women, most women in menopausal transition would benefit from a hormonal top-up, if they choose to have it.

WHAT IS MENOPAUSE IN PLAIN ENGLISH

WHAT IS MENOPAUSE IN PLAIN ENGLISH

Ajumma Wellbeing Clinic is about women’s wellbeing, specifically for those beyond the reproductive stage of their lives. The R&D phase of the project delves into biological, psychological, social, and cultural (Aus-Korean) perspectives. Under the guidance of my science collaborators, I sifted through a lot of information to identify the right information amid not-so-legitimate claims.

Here are some of the basic things I have learned, translated into plain English, as I understand them. Also, the link below summarises them nicely, except for the photo that comes with the link here…

A happy middle-class white couple with no stress in their lives

…as if menopause is only for middle- to upper-class white women in a bob with perfect false eyelashes, happily married to a happy, relaxed white old guy in his white linen shirt, surrounded by a beautifully tidy, dry, mould-free patio, staring into some happy place far ahead. They are also perfectly slim. Ooh, wait, he’s not wearing a wedding ring. God forbid, who is he to her?! I digress. Here is the link.

https://www.healthyhormones.au/c/handouts-4fbd8d/menopause-23adc6e7-06f0-4bb4-9020-a80297519efe


Another link to define and summarise menopause:

https://www.ncbi.nlm.nih.gov/books/NBK507826/


Plan English version of the above link:

https://mdsearchlight.com/womens-health/menopause/?utm_source=pubmedlink&utm_campaign=MDS&utm_content=24984


  • A random white guy in 1821 coined the term ‘menopause’. This French physician wanted a clear medical term for women in the post-reproductive stage. Did any women get to have a say in defining this terminology? Of course not. Unsurprisingly, this ‘clear word’ made things more confusing. This rando’s word has now evolved to refer to Menopause as the one single day – exactly 12 months after the last period. Because perimenopause occurs well before this 12-month date of the last period, many women think they are not in the transition because they are still bleeding. Perimenopause is when a shit ton of symptoms bomb them hard or surreptitiously eat them away bit by bit over a longer period of time. The presentation of these symptoms can be so varied and inconsistent that women often think the symptoms are unrelated to perimenopause. After this single day of the 12th-month, it is called post-menopause until we die.
  • Studying menopause is messy and patchy because this post-reproductive stage has been so neglected by most societies and the scientific world.
  • Menopause has largely been outside the scope of study. Although women have existed alongside men for a long time, most of our ancestors didn’t live long enough to thrive in the post-reproductive age, so there are still many things we don’t know about this stage of women’s lives. What we do know, however, is contentious, and shrouded in misinformation and disinformation.
  • In most cultures until recently, women were considered the same as men, just a smaller, weaker, and inferior version.
  • When people refer to menopause nowadays, including in my project, it often means the whole transition from peri-menopause to post-menopause, which is the second half of their lives.
  • Menopause is a biological process that occurs in every human born with ovaries, and no amount of meditation or CBT (Cognitive Behavioural Therapy) can get people out of menopause.
  • Depending on your age, the current generation (or our parents’) is generally considered the first to outlive the lifespan of our ovaries. The average life expectancy for women is 85, and for men, 80.
  • Our ovaries contain the highest number of eggs while we are in our mothers’ wombs, and we gradually lose eggs thereafter until none remain, on average around 40+ years of age.
  • Perimenopause is when women’s hormones slowly begin to taper off from the reproductive phase. It can start in their 30s, or, in some cases, even in their teens. Every woman’s body does its own thing, and that’s ok. This tapering-off phase can last from several years to over a decade. During this time, their hormones fluctuate drastically, resulting in many subtle and crazy symptoms.
  • Women of colour and/or those with endometriosis/adenomyosis start the menopause transition several years earlier than healthy Anglo-Saxon women, with slightly different symptom profiles, but not enough research has been done to know why or how.

GROWING MEMBERS OF MY COLLABORATING RESEARCHERS

Advocating for women’s health and well-being has become my passion and lifelong pursuit. I wish my mum and all the women in my life had known some of what I have learned. I dream of all women being better educated and empowered. Knowledge is power. Truly. I grow each day, thanks to other women’s deeply shared lived stories and to evidence-based research. Little did I know that researching menopause meant delving into the entire second half of women’s lifespan, encompassing every aspect of human experience.

When I started pondering the concept of menopause in 2024, I thought it would be relatively straightforward. When I started writing grant applications about it, I was surprised by how tricky it was to find a so-called menopause expert in Australia. From my own experience, I knew it involved pain, fatigue, mood, and disrupted immune functions, so based on my experience, I formed my team of researchers I already had relationships with :

Dr Carolyn Berryman (Image credit:

Dr Carolyn Berryman (Clinical Neuroscientist & Senior Physiotherapist)

Jane Miskovic-wheatley

Dr Jane Miskovic-Wheatley (clinical psychologist)

Prof Mark Hutchinson, Dr Carolyn Berryman, Eugenie Lee in his office

Prof Mark Hutchinson, Dr Carolyn Berryman, Eugenie Lee in his office

To the team, Carolyn also brought in Prof Mark Hutchinson, who leads the Neuroimmunopharmacology lab at Adelaide University. His role was to guide me on all aspects of immune regulation and inflammation.

With the support of two successful grants from Creative Australia for the first stage of the project, I embarked on initial research with my collaborators and conducted community interviews with menopausal women with lived experience early this year.

However, within the first few days, it became overwhelmingly evident that I knew very little about menopause, despite being menopausal. Furthermore, my collaborators brought their expertise in their respective fields to the project, but we explored menopause together, approaching it from the peripheries. This was because no one had learned about menopause as a primary subject of research. No one does to this day.

Why? No medical students learn much about menopause during their years of training, possibly less than they do about persistent/chronic pain. Menopause is rarely taught in medical schools worldwide, typically for about 30 minutes over the entire course, or sometimes only as a footnote in some universities. This explains why I couldn’t find a suitable menopause expert before – no clinicians had ever studied menopause as their primary subject because such a subject never existed. It still doesn’t.

No discipline owns menopause. Menopause, as a field of study, is an orphan. Gynaecologists are primarily concerned with the reproductive organs of women in their reproductive years. Endocrinologists deal with hormones, but not with an overarching, vast human experience such as menopause. GPs are better trained to see the full range of human diseases, but, like other medical practitioners, they are simply not taught much about menopause. The very few doctors who are well-versed in supporting menopausal women are those who have done extra training outside their practice. They are self-taught. Thank goodness for these troopers. There are more of them now than a few years ago.

Valid knowledge about menopause is out there, but it is scattered. There is more misinformation about menopause than solid, evidence-based knowledge. Everyone seems to be talking about menopause these days, compared with when I first thought of this topic for my art project two years ago. Part of the collaborators’ and my tasks at this stage of research have been to identify who, what, and where to turn to obtain the right sources to jigsaw-puzzle this enormously complex topic of menopause.

Menopause care is multifactorial – no single discipline, treatment, or approach can address every aspect of women’s post-reproductive lives over their 30-40 years. That is why I had to bring in additional researchers to this project. They are:

Dr jenny Bromberger

Dr Jenny Bromberger (Integrative GP, Woolloomooloo, NSW)

Ann Trager-Spees in her clinic

Ann Traeger-Spees (Sexologist, pelvic physiotherapist, Kaurna/Adelaide, SA)

Prof David MacIntyre

Prof David MacIntyre (Professor of Reproductive Systems Medicine, Adelaide Uni)

So far, my research with them have been incredible. All female researchers passionately bring their lived experience and expertise, and the male researchers bring their allyship and expertise to the project. This project doesn’t just belong to me. It belongs to all of us involved.


ABOUT AJUMMA

Ajumma [Ah‑Joom‑Mah] is a Korean gender‑ and age‑related derogatory term used to depict women in menopause, usually those in heterosexual marriage with a few obligatory children. It is a label for Korean menopausal women, implying they are “over the hill,” “no longer worthy of the male gaze,” “too loud, crazy, outspoken,” or that they’ve “let themselves go” in appearance — stereotypes that reduce them to caricatures rather than people. Today, no woman wants to be called Ajumma, as it is considered beyond the “attractive age.” I suppose “attractive age” must mean the reproductive age, because society still tends to value women most when they fall within that period.

Tem portrait images of asian women, squatting down and posing for the camera, all wearing colourful mismatched clothes with sun visors.

Stereotyped images of Ajumma. Image: Pinterest

Growing up in South Korea, I remember it was still a developing, low-income country. Unlike the current perception, the meaning of Ajumma was quite different back then. From my perspective as a child, I looked up to them, and I needed them to survive. Continue reading →